By Dr. Anup Ramani
Share At:
Google AI ChatGPT Grok Perplexity

Listening Article

AI Summary

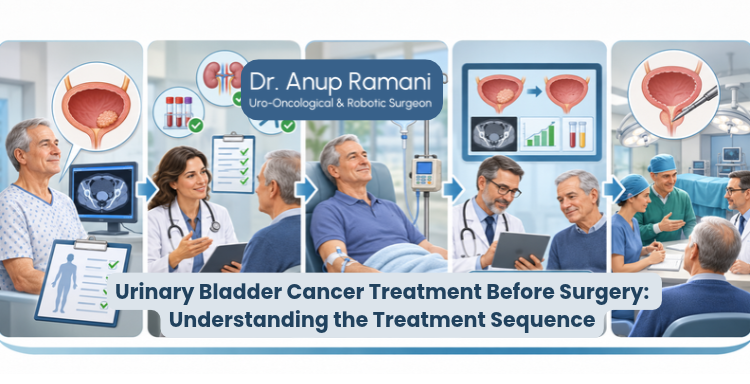
For selected patients with muscle invasive bladder cancer, treatment before urinary bladder cancer surgery, such as chemotherapy before cystectomy, may be recommended as part of a planned sequence rather than an unexplained delay. After diagnosis and staging, a medical oncologist reviews treatment eligibility, general fitness and kidney function before deciding whether this systemic treatment should come before cystectomy. Patients are then monitored during treatment, reassessed for response and surgical readiness, and the surgical team confirms whether the original plan still applies. The exact aim and sequence depend on the individual clinical situation.

Why Treatment Before Bladder Cancer Surgery May Be Recommended

A diagnosis of muscle invasive bladder cancer often brings an expectation of early surgery. So when a treating team recommends treatment before urinary bladder cancer surgery instead, patients and families can feel uncertain about what this means and why it has been proposed for their particular case.

Treatment before urinary bladder cancer surgery follows specific clinical reasoning about the cancer, the patient and the available evidence, rather than scheduling or administrative reasons. This reasoning is shaped collaboratively, through multidisciplinary bladder cancer care involving the surgical and oncology teams, and understanding it can help patients prepare for consultations and ask informed questions.

 
Need More Information?
White Email Us Today!
 

What Does Treatment Before Bladder Cancer Surgery Mean?

Doctors use several terms to describe the timing of cancer treatment relative to surgery. Neoadjuvant treatment refers to systemic treatment given before the main surgery, usually to address cancer cells that may already have spread beyond the bladder at a microscopic level. Perioperative treatment is a broader term covering treatment given both before and after surgery as one coordinated plan. Adjuvant treatment refers to treatment given after surgery, often based on the final pathology report.

Before any of this, most patients will have already had a transurethral resection of bladder tumour, or TURBT, a procedure performed through the urethra to sample and partially remove the tumour for diagnosis and initial staging. Radical cystectomy removes the bladder. Robotic cystectomy planning is considered when that surgical approach is appropriate. TURBT establishes the diagnosis; cystectomy is the definitive surgical treatment that may follow, with or without treatment beforehand.

Neoadjuvant Therapy for Bladder Cancer: Why It May Precede Cystectomy

In appropriately selected patients with muscle-invasive bladder cancer, treatment before surgery is considered because the disease can sometimes extend beyond what imaging and TURBT alone can detect. Addressing this possible microscopic disease before the bladder is removed, and treating the cancer as part of one coordinated approach rather than surgery in isolation, are among the main reasons this sequence is used in patients meeting specific eligibility criteria.

It is important to distinguish potentially operable disease treated with neoadjuvant therapy for bladder cancer from initially unresectable or metastatic disease, which generally follows a different pathway. Shrinkage of the visible tumour is one marker doctors look for, but it is not the only purpose of treatment given before surgery.

What Information Guides Bladder Cancer Treatment Sequencing?

Several pieces of information guide whether treatment before surgery is appropriate for a particular patient:

  • TURBT findings and the detailed pathology report.
  • Whether bladder muscle is present in the specimen and whether it shows tumour involvement.
  • The histological type of the cancer and any relevant variant features.
  • Imaging findings and clinical stage.
  • Whether any lymph nodes appear involved.
  • Kidney function and whether there is any urinary tract obstruction.
  • General health, functional status and other existing medical conditions.
  • The patient’s own priorities and preferences.

When this information is incomplete or unclear, further pathology review or additional investigations may be requested before a final recommendation is made.

Medical Oncology Assessment for Muscle-Invasive Bladder Cancer

Patients referred to a medical oncologist before surgery can expect a structured assessment rather than an immediate start to treatment. This includes a review of the diagnosis and treatment goal, and an assessment of eligibility that takes into account kidney function, hearing, nerve symptoms, relevant heart conditions and overall functional status, since these determine which treatments are suitable. Current medicines and baseline investigations are also reviewed at this visit, distinct from the fitness checks that happen later, closer to surgery.

The oncologist discusses expected benefits, possible side effects and reasonable alternatives. Fitness for systemic treatment and fitness for surgery are related but separate assessments, so suitability for one does not automatically mean suitability for the other.

Chemotherapy Before Cystectomy and Other Treatment Options

Chemotherapy Before Cystectomy

For eligible patients, chemotherapy before cystectomy addresses possible microscopic disease beyond the bladder. Cisplatin based combination chemotherapy is the most established option, based on current international guidance, and is used only in patients who meet the eligibility criteria already outlined at the oncology assessment. Carboplatin is not an automatic substitute for cisplatin in this setting, and unsuitability for cisplatin does not automatically mean unsuitability for surgery itself.

Other Systemic Treatment Approaches for Bladder Cancer

For selected eligible patients, current international guidelines include chemotherapy combined with immunotherapy before surgery, followed by further immunotherapy afterwards. The medical oncologist explains whether this approach is appropriate for the individual patient and available under local approvals.

If Treatment Before Surgery Is Unsuitable

If a patient is not eligible for the treatment initially proposed, the team may reconsider the sequence, proceed to surgery as the primary treatment, discuss other established pathways, or consider clinical trials where relevant. No single alternative suits every patient.

The Treatment Pathway Before Urinary Bladder Cancer Surgery

Step What is reviewed or done What the patient should understand
Diagnosis and staging Pathology, scans and clinical assessment Why the proposed pathway fits the diagnosis
Oncology assessment Treatment eligibility and baseline health Expected benefits, risks and alternatives
Treatment before surgery Systemic treatment and monitoring Who to contact about side effects
Reassessment Response, organ function and surgical fitness Whether the plan needs adjustment
Cystectomy planning Operation, urinary diversion and recovery preparation What surgery and life afterwards may involve

This pathway is a general guide rather than a fixed schedule, and it can change if new findings arise at any stage.

Monitoring During Chemotherapy Before Cystectomy

While receiving treatment before surgery, patients are monitored for symptoms and side effects, with regular checks of blood counts, kidney function, hydration, nutrition and general fitness. The team also watches for infection and other complications. Fever during systemic treatment, severe illness or other urgent symptoms require prompt contact with the oncology team according to its emergency guidance, rather than waiting for the next scheduled visit.

What Our Patients Are Saying

" Dr. Ramani was very professional in his approach. He spent a lot of time to discuss the problem and compassionately handled a very complicated case. He is always accessible and ready to go the extra mile to put the patient at ease. Highly recommended! "
Manish Maheswari
On Google

Reassessment Before Cystectomy: Confirming the Surgical Plan

Once treatment before surgery is complete, the treating teams review what was received, including any interruptions, along with updated imaging where indicated, changes in symptoms, kidney function and blood results, and recovery from treatment related effects. Anaesthetic and surgical fitness are checked again at this stage, since a patient’s condition can change over the course of treatment.

Imaging response is useful, but it does not replace what is learned from surgical pathology once the bladder specimen is examined after cystectomy. If progression, complications or declining fitness are identified during this review, the plan may be revised.

Multidisciplinary Bladder Cancer Care Coordination

Multidisciplinary bladder cancer care coordinates the proposed sequence between the surgical and oncology teams, bringing together the urological surgeon, the medical oncologist, a radiologist and a pathologist, the anaesthesia team, and specialist nurses or stoma care professionals, with others involved when needed. These professionals exchange information on treatment completion, complications, reassessment findings and overall readiness for surgery.

Where Robotic Cystectomy Planning Fits in the Sequence

Robotic cystectomy planning considers the suitability of the surgical approach, urinary diversion options, previous operations, surgical fitness and recovery preparation. A robotic approach does not replace systemic treatment when indicated or determine the overall treatment sequence.

 
Let’s Discuss! Request a Call Now!
White Call Now!
 

Questions to Ask About Treatment Before Bladder Cancer Surgery

  • What is the goal of treatment before my operation?
  • Is my diagnosis and stage sufficiently established?
  • Why is this treatment suitable for me?
  • What alternatives are reasonable if I cannot receive it?
  • Who will monitor side effects and urgent problems?
  • How will my response and fitness be reassessed?
  • What findings could change the plan?
  • When will the surgical team review me again?
  • What urinary diversion options should I understand?
  • Could further treatment be discussed after surgery?

Dr. Anup Ramani: Bladder Cancer Surgery and Treatment Planning in Mumbai

Dr. Anup Ramani is a uro oncological surgeon in Mumbai with over two decades of experience in robotic surgery for urological cancers, including robotic radical cystectomy for bladder cancer. Where treatment before surgery forms part of a patient’s plan, he coordinates with the managing oncologists and reassesses surgical readiness before proceeding.

Conclusion: Treatment Before Urinary Bladder Cancer Surgery

Treatment before urinary bladder cancer surgery can be a deliberate, well reasoned part of the overall care plan for selected patients with muscle invasive bladder cancer, rather than a departure from it. Understanding the goal of each step, who coordinates it, and what reassessment is needed before cystectomy can help patients feel more informed through this pathway. Patients seeking urinary bladder cancer surgery in Mumbai can arrange a consultation to discuss their diagnosis and proposed treatment sequence with their treating surgical and oncology specialists.

FAQs on Treatment Before Urinary Bladder Cancer Surgery

To address possible microscopic disease beyond the bladder, as part of a coordinated treatment approach, in patients meeting the relevant eligibility criteria.

No. Neoadjuvant treatment is given before surgery, while adjuvant treatment is given afterwards, often guided by the final pathology findings.

No. The decision depends on cisplatin eligibility, overall fitness and the specific features of the cancer.

The team may reconsider the sequence, proceed with surgery as the primary treatment, or discuss other pathways or trials, depending on the situation.

Through a combination of imaging, symptom review and blood tests during treatment, alongside clinical reassessment before surgery.

When treatment has been planned before radical cystectomy, a good response on imaging usually does not remove the need for the operation. Scans cannot reliably exclude microscopic remaining cancer. Any change to the planned pathway requires specialist multidisciplinary review.

No. The surgical approach does not determine whether treatment before surgery is needed.

After reassessment of treatment response, recovery, organ function and overall surgical fitness, in coordination between the oncology and surgical teams.

PARTIAL PENECTOMY
  • Partial penectomy is done in cases where glans and distal penis is involved with carcinoma. 
  • Partial penectomy is a type of organ-preserving surgery. Preservation of sexual and micturational function depends on the surgical dissection and reconstruction of residual urethra.
Kidney Stone Removal
  • Patients who develop stones in the kidney or ureter, often experience severe pain.
  • This condition usually needs a procedure to remove the kidney stones.
  • This procedure is called ureteroscopy and is performed very commonly.
  • It does not require any cuts and hence it is painless.
  • The procedure is performed with an endoscope inserted through the penis under spinal anesthesia.
  • The scope is inserted through the penis into the kidney and stones are dissolved with a laser.
  • The procedure takes about 40-50 minutes. 
  • A catheter (urine pipe) is kept after the procedure to drain the bladder. A stent is kept in the kidney at the same time.
  • Patient is mobile and walking in the room the same evening.
  • Hospital stay is one night and patient is discharged the next day after removal of the catheter.
  • Patient has to come back after six weeks to remove the stent in the kidney.
  • Patients can resume office a week after surgery and heavy activities like running, weight lifting, a month after the procedure.
  • We offer fixed packages for this procedure which can be obtained by calling our helpline +91 9967666060.
  • Men with an enlarged prostate, which is a normal ageing changes, often experiencing difficulty passing urine. This condition usually needs a procedure to trim the prostate and relieve the blockage.
  • This procedure is called TURP and is performed very commonly.
  • It does not require any cuts and hence it is painless.
  • The procedure is performed with an endoscope inserted through the penis under spinal anaesthesia.
  • The overgrown prostate is dissolved with a laser bloodlessly.
  • The procedure takes about 40 minutes.
  • A catheter (urine pipe) is kept after the procedure to drain the bladder.
  • Patient is mobile and walking in the room the same evening.
  • Hospital stay is two nights and patient is discharged with the catheter, which is removed after 4 days.
  • Patients can resume office a week after surgery and heavy activities like running, weight lifting, a month after the procedure.
  • We offer fixed packages for this procedure which can be obtained by calling our helpline +91 9967666060.
ROBOTIC ADRENALECTOMY FOR ADRENAL GLAND TUMOUR
  • Robotic adrenalectomy is a sophisticated, complex surgery and it is very important that an experienced surgeon performs this surgery to avoid major complications.

  • Once the anesthesia is done, and patient positioned, three micro cuts (3mm each) are made in the patient’s abdomen.

  • The arms of the Da Vinci robot are connected to the cuts via ports (tubes).

  • Dr. Ramani then sits in the controlling console to perform the surgery.

  • On an average, a robotic adrenalectomy takes one hour.

  • The surgery is almost completely bloodless and there has never been any need to transfuse blood after surgery.

  • A urine catheter and bag to drain the bladder is inserted during surgery.

  • A tiny drain pipe may be inserted in the surgical side of the abdomen, connected to a bag.

  • Patient is kept nil-by-mouth the day of the surgery, with IV fluids. Sips of water are started the next day and solid food by day three.

  • The drain pipe, if kept, is removed in the room on day 2 after surgery.

  • The catheter is removed on day two after surgery.

  • Total hospital stay for robotic adrenalectomy is 4 nights (including night before surgery).

  • Post discharge, a doctor from the surgical team visits the patient at home/ hotel room once every day.

RETURN TO ACTIVITY
  • On the day of discharge, patient is totally self-sufficient. They are able to walk freely without any pain, dress themselves, shower, toilet and they do not need to hire any nurse or help at home. Almost all patients are back to work within 2 weeks of surgery.

  • Heavy activities like running, weight lifting can be resumed after a month

FOLLOW UP AFTER SURGERY
  • Follow up after an adrenalectomy is in the form of CT scans, once a year for 5 years.
    Local patients usually meet Dr. Ramani after two weeks to discuss report.

  • Outstation patients are counselled on a phone consultation.

ROBOTIC SURGERY FOR BLADDER CANCER
  • Dr. Ramani is one of the very few surgeons in India who has the expertise to perform a robotic surgery for bladder cancer, which includes removing the urinary bladder and reconstructing a new bladder robotically.
  • Robotic radical cystectomy is an extremely sophisticated, complex surgery and it is very important that an experienced surgeon performs this surgery to avoid major complications.
  • Once the anaesthesia is done, and patient positioned, six micro cuts (3mm each) are made in the patient’s abdomen.
  • The arms of the Da Vinci robot are connected to the cuts via ports (tubes).
  • Dr. Ramani then sits in the controlling console to perform the surgery.
  • On an average, a robotic radical cystectomy with an ileal conduit takes 3-4 hours.
  • The surgery is almost completely bloodless and there has never been any need to transfuse blood after surgery.
  • A urine catheter and bag to drain the new bladder is inserted during surgery.
  • Two tiny drain pipe in inserted in the surgical side of the abdomen, connected to a bag.
  • Patient is kept nil-by-mouth for 4 days after surgery with IV supplementation of patient’s daily requirements of calories, fats, carbohydrates, proteins and electrolytes.
  • The drain pipes are removed in the room on day 3-5 after surgery.
  • Total hospital stay for radical cystectomy is 8 nights (including night before surgery).
  • Post discharge, a doctor from the surgical team visits the patient at home/ hotel room once every day.
RETURN TO ACTIVITY
  • On the day of discharge, patient is totally self-sufficient. They are able to walk freely without any pain, dress themselves, shower, toilet and they do not need to hire any nurse or help at home.
  • Almost all patients are back to work within 6 weeks of surgery. Heavy activities like running, weight lifting can be resumed after two months.
FOLLOW UP AFTER SURGERY
  • Follow up after a radical a cystectomy is in the form of CT scans, once a year for 5 years.

  • Histopathology report: Local patients usually meet Dr. Ramani after two weeks to discuss report.

  • Outstation patients are counselled on a phone consult. Depending on the report, patient may or may not need chemotherapy after surgery.

  • If chemo is needed, patients may choose to get it done with a medical oncologist of their choice or avail the services of one of the four medical oncologists on our team.

ROBOTIC RADICAL/PARTIAL NEPHRECTOMY FOR KIDNEY CANCER
  • Robotic partial nephrectomy is a sophisticated, complex surgery and it is very important that an experienced surgeon performs this surgery to avoid major complications. Robotic radical (total) nephrectomy is
  • relatively easier but still requires significant experience to consistently deliver results.
  • Once the anaesthesia is done, and patient positioned, five micro cuts (3mm each) are made in the patient’s abdomen.
  • The arms of the Da Vinci robot are connected to the cuts via ports (tubes).
  • Dr. Ramani then sits in the controlling console to perform the surgery.
  • On an average, a robotic radical nephrectomy takes one hour and a robotic partial nephrectomy takes about an hour and half.
  • The surgery is almost completely bloodless and there has never been any need to transfuse blood after surgery.
  • A urine catheter and bag to drain the bladder is inserted during surgery.
  • A tiny drain pipe in inserted in the surgical side of the abdomen, connected to a bag.
  • Patient is kept nil-by-mouth the day of the surgery, with IV fluids. Sips of water are started the next day and solid food by day three.
  • The drain pipe is removed in the room on day 3 after surgery. The catheter is removed on day two after surgery.
  • Total hospital stay for radical/partial nephrectomy is 4 nights (including night before surgery).
  • Post discharge, a doctor from the surgical team visits the patient at home/ hotel room once every day.
RETURN TO ACTIVITY
  • On the day of discharge, patient is totally self- sufficient. 
  • They are able to walk freely without any pain, dress themselves, shower, toilet and they do not need to hire any nurse or help at home. 
  • Almost all patients are back to work within 2-3 weeks of surgery.
  • Heavy activities like running, weight lifting can be resumed after a month.
FOLLOW UP AFTER SURGERY
  • Follow up after a radical/partial Nephrectomy is in the form of CT scans, once a year for 5 years.
  • Local patients usually meet Dr. Ramani after two weeks to discuss report. 
  • Outstation patients are counselled on a phone consultation.